What I Do When My Doctors Don’t Listen

As much as I want to believe my doctors are beyond brilliant and can do anything, they are people too. Much like me, they have good days and not-so-great ones.

What are the signs your doctor isn’t listening?

  1. Constant interruptions.
  2. Fidgeting.
  3. There but not there.
  4. Aggressive body language.

I make sure my doctor is listening by:

  1. Being prepared.
  2. Being courteous.
  3. Rewinding the conversation.
  4. As a last step, change doctors.

Rather than shrink back from having a “tough” conversation with a doctor, it is critical to do just that. Often these types of conversations, rather than ending a relationship with a doctor, strengthen it.

Lynch Syndrome and the Challenge of Getting a Diagnosis

Lynch Syndrome often goes unnoticed in the general population. This is because many individuals affected may not have a family history of cancer or may show unusual symptoms, making it hard to spot without genetic testing.

We need doctors and healthcare teams to know more about Lynch Syndrome, provide more accessible ways for people to get genetic testing, and offer simpler ways to find out if someone might have Lynch Syndrome and if they’re at risk.

Genomic Landscape of Lynch Syndrome Colorectal Neoplasia Identifies Shared Mutated Neoantigens for Immunoprevention

Report a focused somatic mutation and frameshift-neoAg landscape of microsatellite loci from colorectal polyps without malignant potential (PWOMPs), precancers, and early-stage cancers in LS carriers.

Conclusions

Shared frameshift-neoAgs are generated within unstable microsatellite loci at initial stages of LS carcinogenesis and can induce T-cell responses, generating opportunities for vaccine development, targeting LS precancers and early-stage cancers.

https://www.sciencedirect.com/science/article/pii/S0016508524000520

Hereditary Cancer, red flags, and how it impacts screening!

Most cancer is not inherited in families and occurs sporadically, as a result of random changes in our cells over time.  However, approximately 10% of cancer is hereditary and is due to a genetic mutation that has been passed down in the family, increasing the risk for certain cancers to develop. 
https://www.cgaigc.com/post/hereditary-cancer-red-flags-and-how-it-impacts-screening

Finding the missing 95%: Unlocking the potential of Lynch syndrome services

In recent years, breakthroughs in genetics and DNA testing have revolutionised healthcare, especially in cancer diagnosis, treatment, and care. By examining a person’s genes, we can now identify people at higher risk of developing certain cancers.

This allows healthcare providers to detect cancers at an earlier stage and make informed decisions about cancer management and surveillance. Crucially, they can also offer more effective personalised treatments and prevention strategies based on the patient’s genetic profile.

Report found:

  • There have been significant improvements in genetic testing for bowel cancer patients, with an average of 9 in 10 newly diagnosed bowel cancer patients being tested over the last financial year, but workforce and capacity issues are still barriers. 
  • Half of health authorities who responded, reported that family members of people with Lynch syndrome aren’t offered letters they can take to their GP, which is one route to accessing genetic counselling and testing. 
  • A postcode lottery for life-saving routine surveillance colonoscopies exists. Although surveillance is offered to all Lynch syndrome patients in England through the Bowel Cancer Screening Programme, only 6 in 10 health authorities across Scotland, Wales and Northern Ireland offer surveillance colonoscopies in line with clinical guidance. 
  • Major gaps in data collection and reporting on Lynch guidance and services are holding back Lynch syndrome care. 

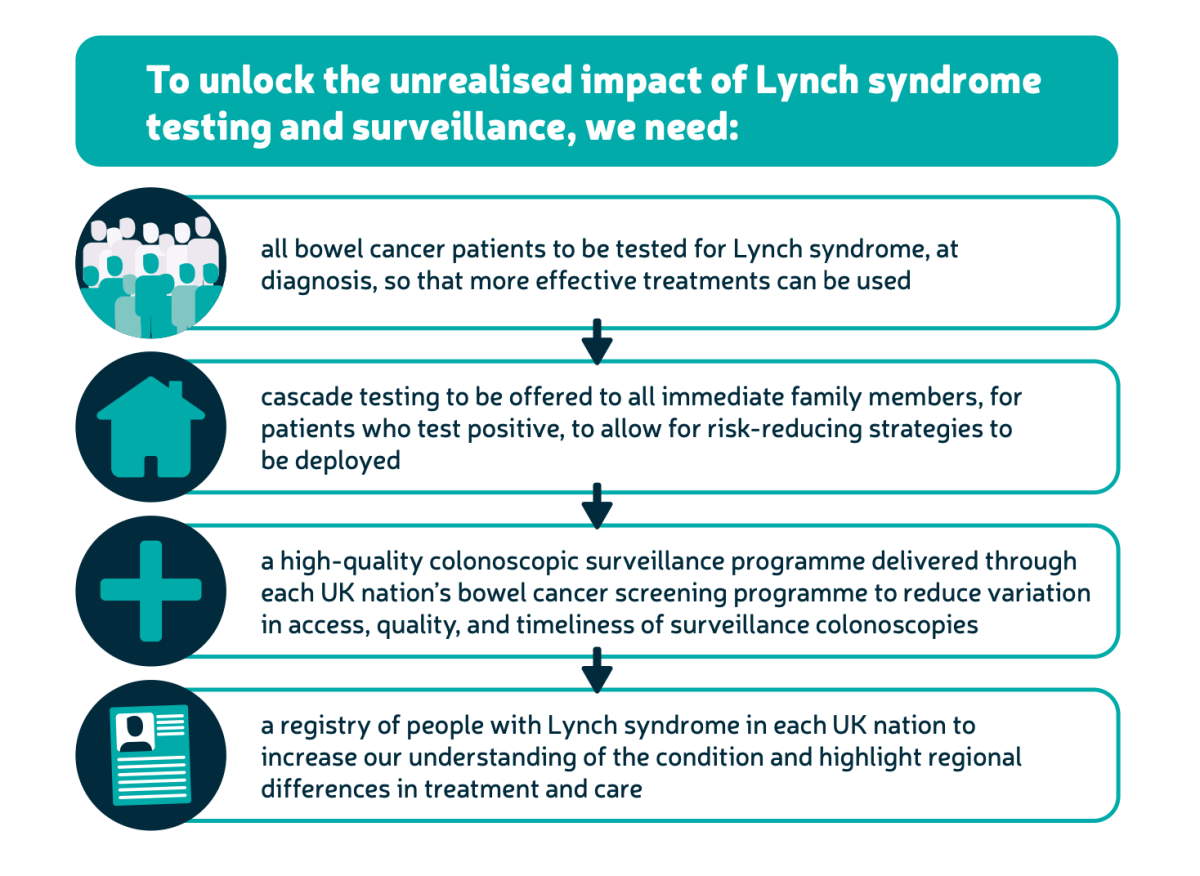
Testing all newly diagnosed bowel cancer patients for Lynch syndrome and implementing routine colonoscopic surveillance are crucial steps in meeting the early diagnosis goals set by governments and health services nationwide.

Study Finds New Role For Vitamin D In Cancer Treatment

“These results suggest that vitamin D supplementation in patients with lower levels of vitamin D may reduce peripheral neuropathy, and particularly high-grade peripheral neuropathy, which would improve these patients’ long-term quality of life,” said senior researcher Daniel L. Hertz, PharmD, PhD, of the University of Michigan College of Pharmacy.

Hereditary Cancer Rounds – Describing the Real World Experience of Implementing a Pre-test GC Portal

Similar Population to Ireland

Had similar issues to Ireland…long waiting list for Genetic Counselling etc. Using technology they have improved their situation.

The Hereditary Cancer Program provides genetic counselling and genetic testing for BC/Yukon residents who may have inherited an increased risk for certain types of cancer.

PROTECTOR study (UK)

Current research points towards ovarian cancer beginning in the fallopian tube and not in the ovary itself.

This is where PROTECTOR comes in, with the theory being that removing the tube alone will help prevent cancer while being able to preserve fertility and avoid early menopause which comes with symptoms and long term health issues like hot flushes, sweats, mood changes, thinning of the bones, memory problems, higher risk of heart disease, and reduced libido.

Lynch Syndrome as a Family Diagnosis

It’s a Family diagnosis.

Open communication is important.

Knowledge is power.

Why would you not want to know???

Serendipity Strikes: How Pursuing Novel Hypotheses Shifted the Paradigm Regarding the Genetic Basis of Colorectal Cancer and Changed Cancer Therapy

Discoveries enabled better understanding of how the DNA mismatch repair (MMR) system not only recognises DNA damage but also responds to damage by DNA repair or by triggering apoptosis(cell death) in the injured cell. 

What has happened over the past 37 years was not predictable when this journey began, but it does speak to the power of careful scientific experimentation, following the facts, perseverance in the face of opposition, and the willingness to think outside of established paradigms.

The conclusion that CRCs with MSI responded differently to classical cytotoxic chemotherapy than did non-MSI CRCs and eventually, the key clinical paradigm shift was the discovery of ICT(Immune checkpoint therapy and its unique effect on tumours with MSI.

Some of these concepts required brilliant thinking and interpretation and others seemingly announced themselves after the correct understanding of an unexpected observation. Since this astonishing series of events unfolded over about four decades, there is hope that this remarkable progress will continue into the future.

https://link.springer.com/article/10.1007/s10620-023-08006-z#Sec18
