Cured, but at what cost?

Being told you are cancer free doesn’t mean the consequences of treatment disappear.

The fatigue, digestive issues, pain, anxiety and the daily adjustments nobody sees, the world moves on, and you’re expected to be happy because you’re still here, but what happens when the treatment ends, and the real work of living with its consequences begins?

What does good cancer care look like after treatment? or more importantly my question is – Why does our healthcare system measure the success of cancer treatment by survival, but so rarely measure the social, physical and emotional consequences of living beyond cancer?

https://lnkd.in/p/eBd-eHF7

Patient Participation….

There are many forms of patient participation (also referred to as patient engagement, patient involvement, patient partnership, PPI, PPEI) and each method can bring something valuable. But these methods are not all the same, and we have to look carefully what a specific PPI setup actually can and cannot provide.

That question (what type of ‘patient input’ a specific PPI set up provides) should be answered not just by the research team organising the ‘patient input’, but also by the patients who are involved (and maybe even by patients who were NOT involved!). Their answers are likely to differ.

The bar for calling something ‘patient participation’ can be remarkably low.

If every form of consultation is labelled ‘patient participation’, the term stretches until it covers everything and distinguishes nothing.

Is it quicker and easier to prescribe a medicine or book a patient for surgery?

As part of defensive practice, many doctors intervene with surgery or medications – that way they can say that they tried their best.

Surgeries and medicines with limited potential benefit add significantly to the cost of healthcare.

It’s a sad reality of clinical practice where time spent with a patient is a KPI, that it is quicker and easier to prescribe a medicine or book a patient for surgery.

Are many surgical interventions are little better than placebo?

https://www.economist.com/science-and-technology/2026/09/23/many-surgical-interventions-are-little-better-than-placebo

Gynecologic Cancer Awareness Month

Uterine cancer is the most common gynecologic cancer in many high-income countries. In lower-income countries, cervical cancer continues to carry the greatest gynecologic cancer burden—and the global community is working toward changing that.

But wherever you live, one message matters: unexpected or abnormal bleeding needs a proper medical work-up.

Bleeding after menopause is never normal. Before menopause, bleeding that is unusually heavy, prolonged, between periods, or otherwise different from what is normal for you should be discussed with a healthcare professional.

Don’t simply “wait and see.” Don’t assume it’s just menopause, hormones, or your period. Get it checked.

There is no routine screening test for uterine cancer, so recognizing symptoms and seeking appropriate evaluation matters.

Simple test could take the pain out of womb cancer check

The DETECT study – as it is known – was designed to assess whether these simple, non-invasive tests could accurately identify women at risk while safely reassuring others.

Postmenopausal bleeding currently triggers urgent investigations for possible cancer, often involving a series of uncomfortable, invasive and costly tests, despite only 5 – 10% of these women receiving a cancer diagnosis. 
 
🏥 The study of more than 1,800 women attending Greater Manchester hospitals with postmenopausal bleeding showed that the test, which checks vaginal fluid and urine samples, detected womb cancer with high accuracy.

The findings suggest the approach could become a valuable triage tool, helping clinicians decide which women need urgent invasive investigations while providing reassurance for many others.

Don’t wait. Get it checked

Around one in ten bowel cancer diagnoses in Ireland is now to someone under 50, and cases in that age group have almost doubled over the last 25 years. In the US, it’s now the leading cause of cancer death in men aged 20 to 49 and the second-leading cause in women the same age.

BowelScreen still starts at 57. Extending it to 50 was approved in April, but the Department of Health says the full rollout will take years.

Signs of good gut health include comfortable digestion; regular and easy bowel movements; minimal bloating; no excessive gas. A deviation from those might indicate all is not well. 

In the meantime, a sudden change in your bowel habits that doesn’t settle, or any blood in your stool, is a reason to see your GP without delay, whatever your age.

https://www.irishtimes.com/health/your-wellness/2026/09/22/why-your-gut-microbiome-is-important-for-good-health-and-how-to-spot-signs-of-trouble-within

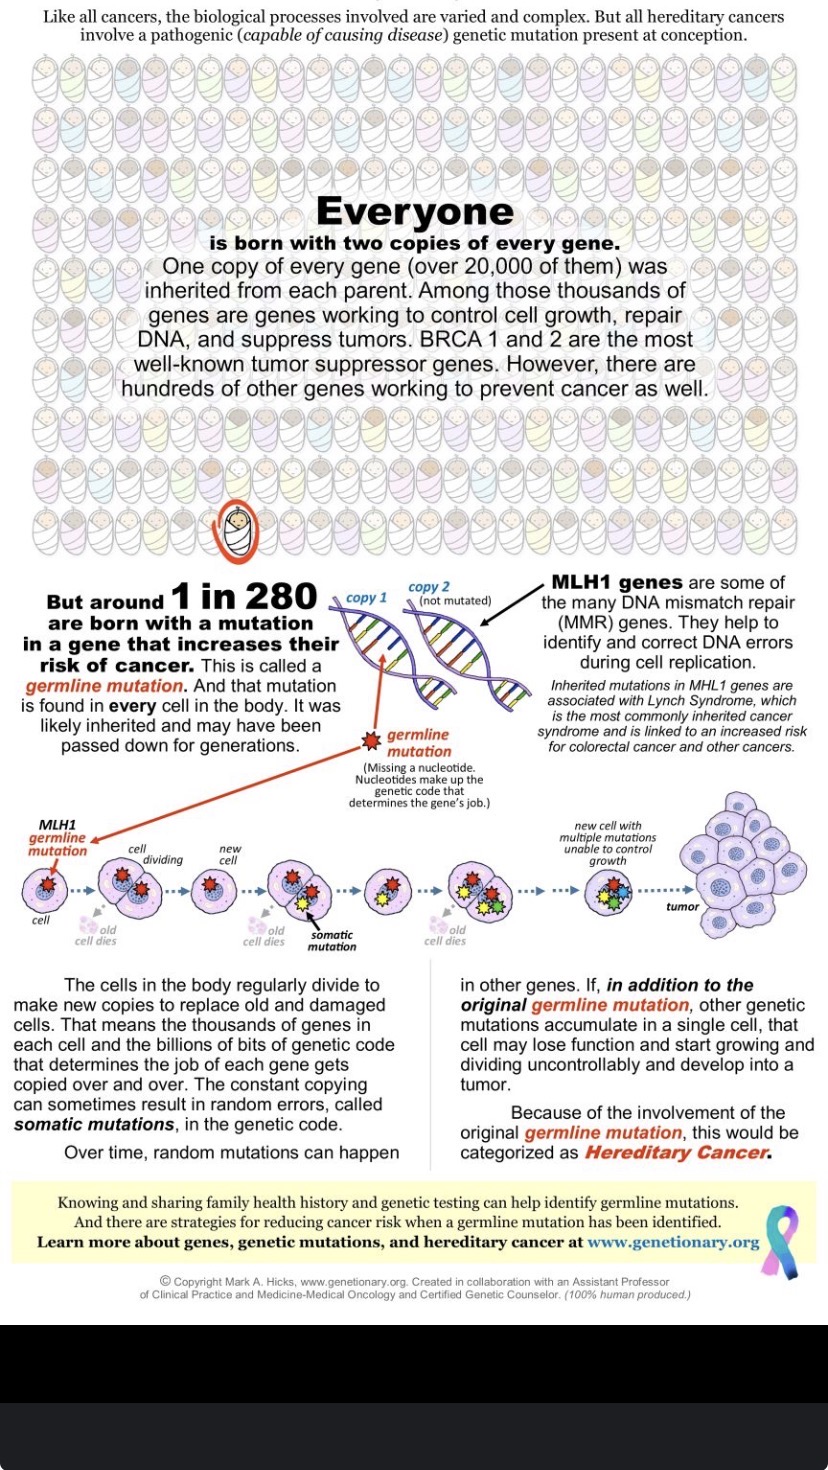
Understanding Cancer Genetics and Hereditary Cancer Risk

https://www.nature.com/articles/s41431-026-02212-9

What is This About?

This article discusses how scientists have discovered that some cancers run in families due to inherited genetic changes. It explains how this knowledge is changing how doctors test for, treat, and prevent cancer.

Key Historical Milestones
  • 1971: Scientists realised that cancer typically requires two genetic “hits” (mutations) to develop, explaining why some families have more cancer cases
  • 1980s-1990s: Researchers identified specific genes that, when mutated, dramatically increase cancer risk (like BRCA1, BRCA2, and others)
  • Today: Doctors now use genetic testing to identify people at high risk and personalise their cancer prevention and treatment plans
The Big Shift: Connecting Two Worlds

Historically, scientists studied:

  1. Somatic mutations (cancer-causing changes that occur only in tumour cells)
  2. Inherited mutations (genetic changes passed down through families)

These were studied separately. Now they’re integrated: if a tumour shows certain genetic changes, doctors test whether the patient inherited that same mutation—which could affect treatment options and what other cancers they might develop.

Current Challenges
  • Many cases remain unexplained: Even with advanced testing, we still don’t know why many families have elevated cancer risk
  • Rare genetic variants: New testing reveals many rare mutations whose danger level is unclear
  • Need for standards: Hospitals need to agree on testing procedures, how to interpret results, and what to tell patients
Emerging Tools and Solutions
  • Polygenic risk scores: Mathematical models predicting cancer risk based on multiple genetic factors
  • Liquid biopsies: Blood tests to detect cancers earlier
  • Advanced sequencing: New technologies to find previously unknown cancer genes
The Human Side

The article emphasises that genetic testing isn’t just scientific—it affects quality of life, family planning decisions, and emotional well-being of people carrying these mutations.

Bottom Line

Hereditary cancer genetics is rapidly evolving, offering better ways to identify at-risk individuals, prevent cancers, and tailor treatments—but significant work remains to make these advances accessible to everyone.


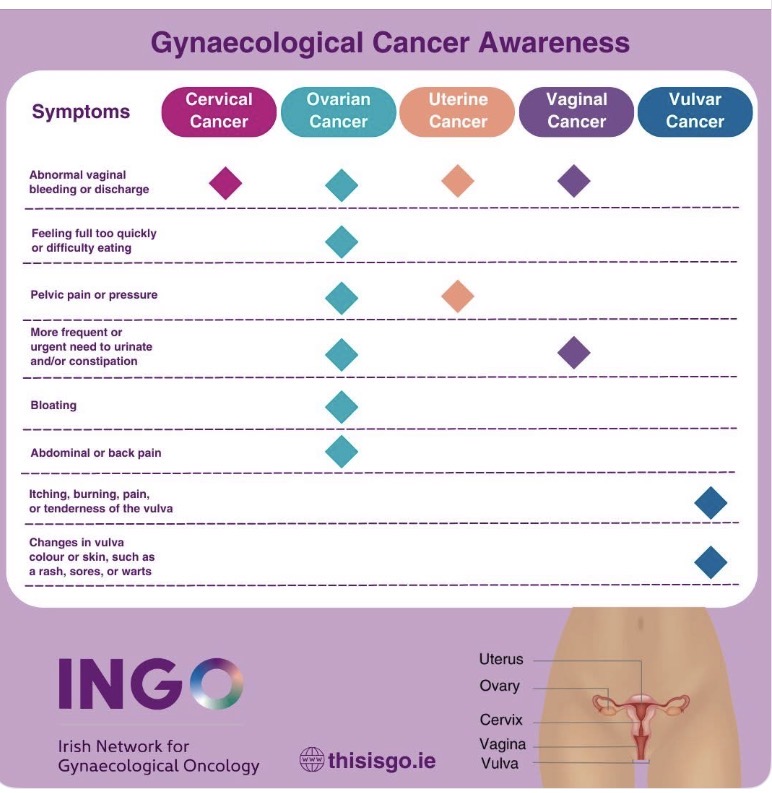
Today is World Gynecologic Oncology Day.

Check out the 5 Gynae Cancers and the symptoms associated with each one.

Testing is the entry point. Prevention is the destination.

Genetic counselling, risk assessment, surveillance, psychological support, risk-reducing surgery and cascade testing all need to sit within a pathway that allows our community to move from knowing about their risk to doing something about it.

These pathways cannot exist solely within individual hospital specialties. They need to connect hospitals, community and primary care services, with clear responsibility for what happens next.

We need to think less about solely how many people we test and more about how many people identified at increased risk actually reach an appropriate preventive intervention, and how we can match each person with the best individual strategy for them.

https://www.sciencedirect.com/science/article/abs/pii/S1048891X26004299

This narrative review synthesises gene-specific counselling, tumour-germline interpretation, and implementation strategies into a clinically oriented pathway from diagnosis to prevention for patients and relatives.