Blog

What we measure, we can improve.

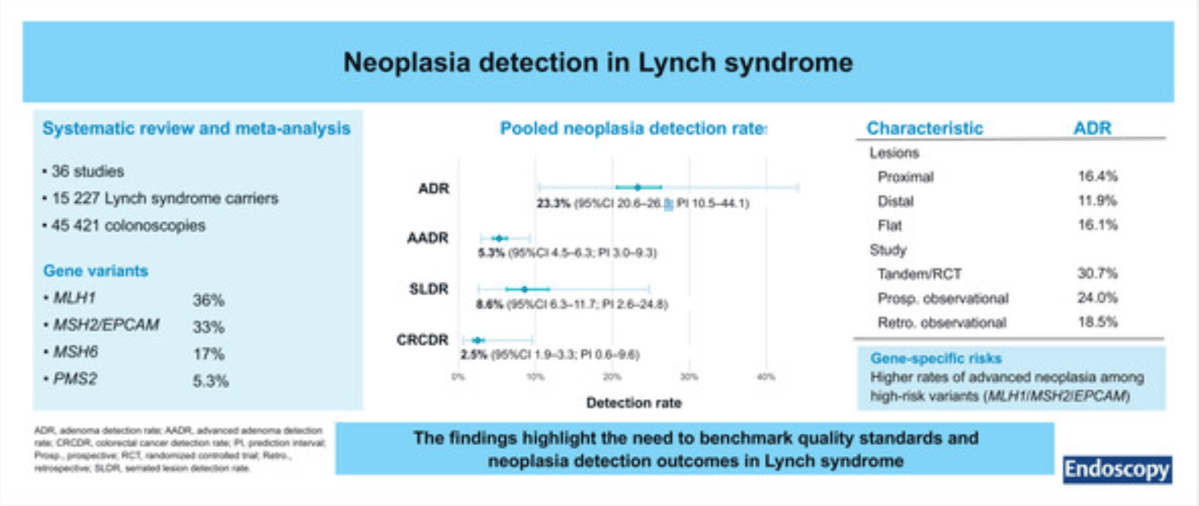
Contemporary trials consistently achieve ADRs around 30% (including the recently published CADLY2 trial from Robert Hüneburg), supporting a provisional minimum ADR benchmark of 25% for colonoscopy surveillance in Lynch syndrome carriers with an intact or near-intact colon.

This is not an aspirational target, but a pragmatic starting point to identify underperformance, drive quality improvement, and ultimately test whether better colonoscopy translates into fewer post-colonoscopy CRCs.

Time to benchmark adenoma detection in Lynch syndrome surveillance.

https://www.thieme-connect.com/products/ejournals/abstract/10.1055/a-2934-4134

Validation is now feasible. The English National Lynch Syndrome Programme provides an ideal platform, combining systematic carrier identification, standardised pathways, and prospective data capture.

It could determine whether ADR, alone or integrated with other indicators, predicts PCCRC in real-world surveillance. Such validation should predefine eligible procedures, account for clustering by patient and endoscopist, examine temporal changes, and evaluate whether improvement in ADR is accompanied by reductions in advanced neoplasia and PCCRC rather than merely increased detection of diminutive lesions over time.

The field should move beyond asking whether colonoscopy “works” in Lynch syndrome and define the measurable conditions under which it most effectively prevents cancer.
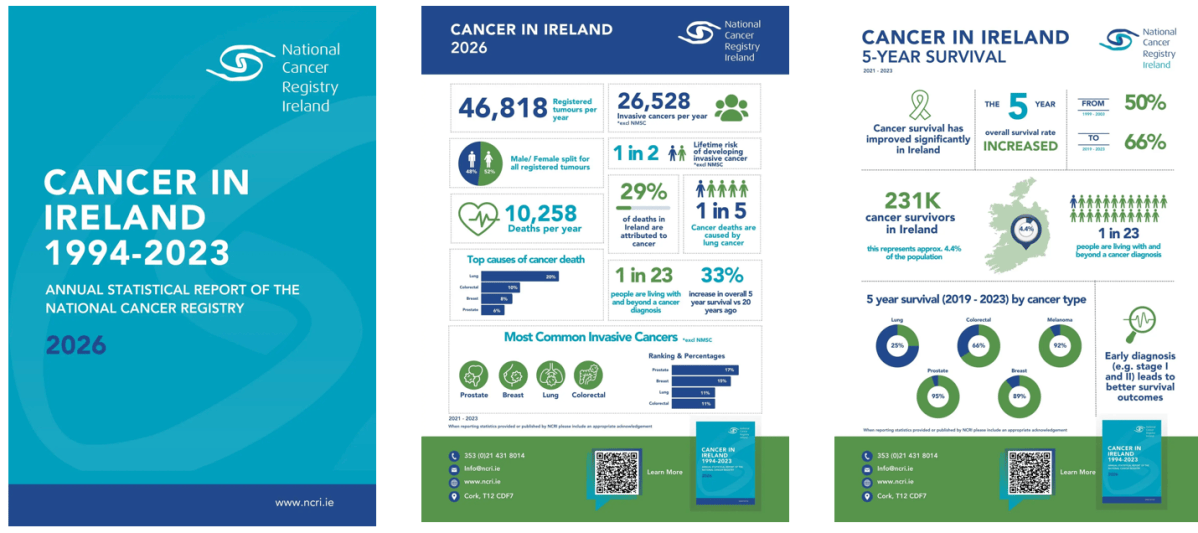

Cancer in Ireland 1994-2023

Annual Statistical Report 2026 has just launched.

Cancer outcomes in Ireland show sustained improvement across three decades:

  • More than 30 years of NCRI data show sustained improvements in cancer survival and reduced mortality
  • Improvements reflect progress in earlier diagnosis, and significant advances in treatment
  • Survival rates for some cancers can be as high as 95% five years after diagnosis
  • Rising baseline numbers are mostly a factor of a growing and ageing population – not a significant increase in population risk

https://www.ncri.ie/en/reports-publications/reports/cancer-in-ireland-1994-2023-annual-statistical-report-of-the-national

Colonic Polyp Regression After Nous-209 Cancer Immunotherapy: A Clinical Trial Case Report

https://innovationsjournals-jipo.kglmeridian.com/view/journals/jipo/9/4/article-p124.xml

What was studied: Doctors treated a patient with an experimental cancer vaccine called Nous‑209 along side pembrolizumab, a standard immunotherapy drug that works by “releasing the brakes” on the immune system so it can attack cancer.

Who it was for: The patient had a type of bowel (colorectal) cancer known as “dMMR” — a cancer with faulty DNA repair machinery. These tumours make a lot of abnormal proteins, which makes them easier for the immune system to recognise. This patient also had many benign (non-cancerous) growths, called polyps, in the bowel — some of which could eventually turn into cancer.

What happened:

  • The patient’s cancer disappeared completely on clinical assessment (a “complete clinical response”).
  • The number of benign polyps dropped substantially — something not clearly seen before with immunotherapy alone.

Why this matters: The vaccine appears to boost the immune system so strongly that it not only attacks the cancer, but also clears away pre-cancerous growths. In theory, this could:

  • Lower the chance of the cancer coming back
  • Stop new polyps forming
  • Offer a form of “immunoprevention” — using the immune system to prevent cancer before it develops

This could be especially valuable for people with dMMR cancers (such as those with Lynch syndrome) and for people with polyposis syndromes, who develop large numbers of polyps and face a high lifetime risk of bowel cancer.

Important caution: These results come from just one patient. A single case cannot prove that the treatment works reliablyor safely for others — it may have been a one-off response. Larger clinical trials and laboratory studies are needed toconfirm the findings and to understand exactly how the treatment produces these effects.

BowelScreen

Free Bowel cancer screening is intended for people without symptoms. FIT looks for blood in a small stool sample and helps identify who may need further investigation.

Ireland: Ages 57-71 – Screening uptake 46%.

UK: Ages 50-74 – Screening uptake 65%

https://lnkd.in/p/d68vCsYF

The Emotional Weight of Cancer Screenings and Appointments

Time for yet another appointment.

  • Another doctor
  • Another screening
  • Another test
  • More waiting
  • More anxiety
  • More stress
  • More unknown

“Don’t feel weak or weird or think that you shouldn’t be having any feelings thoughts or emotions as you get ready for these appointments as you wait on results that is normal and completely understandable.”

https://oncodaily.com/voices/jj-singleton-575240

Help Us Design a New Support App for Cancer Patients

We need to remember what sits behind every number:

Wide variations in delivery of cancer treatment, data shows.

From the patient side, these aren’t just percentages or performance indicators, BUT they are people waiting for treatment, living with uncertainty and wondering when their care will begin.

https://www.rte.ie/news/health/2026/0826/1589223-cancer-treatments-ireland

Why We Advocate….

After being diagnosed, Jennifer and Thrisha quickly realized a shocking truth—finding a doctor who is knowledgeable about Lynch Syndrome is extremely difficult. Both have encountered medical professionals who:

  • Provided inaccurate information about proper screening protocols for Lynch Syndrome.
  • Had to look up information about Lynch Syndrome during their appointments.
  • Medical team is simply unfamiliar with the condition altogether.

This lack of awareness, even among healthcare professionals, is frightening. The knowledge gap in the medical community is putting lives at risk. That’s why Lynch Syndrome Awareness isn’t just about educating the public—it’s also about educating healthcare professionals.

Many Cancers begin with vague, non-specific symptoms

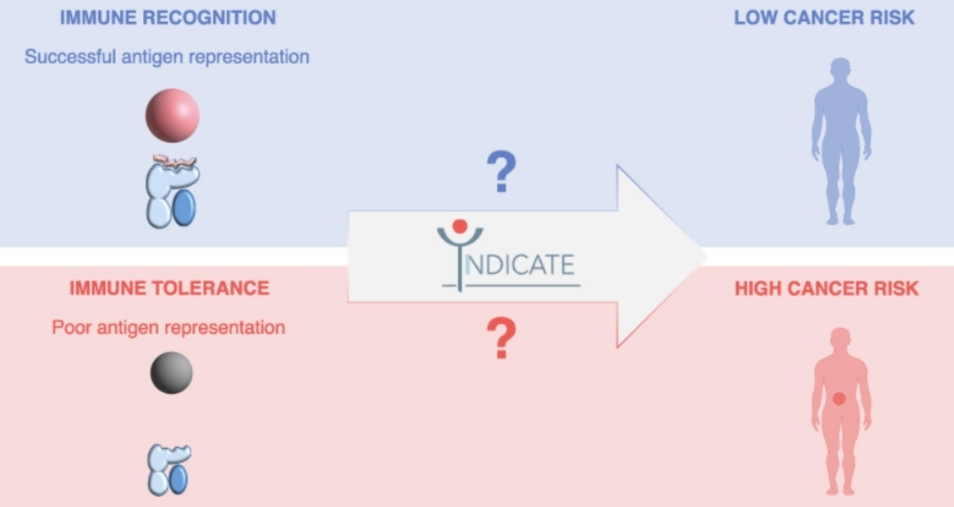
Why Do Cancer Risks Differ Between People With The Same Lynch Syndrome Gene Variant? 🧬

The INDICATE study explores whether HLA type, a key factor in immune recognition, may influence cancer risk and age of onset in Lynch syndrome

ABSTRACT

Lynch syndrome (LS) is the most common inherited cancer syndrome. It is inherited via a monoallelic germline variant in one of the DNA mismatch repair (MMR) genes. LS carriers have a broad 30% to 80% risk of developing various malignancies, and more precise, individual risk estimations would be of high clinical value, allowing tailored cancer prevention and surveillance. Due to MMR deficiency, LS cancers are characterized by the accumulation of frameshift mutations leading to highly immunogenic frameshift peptides (FSPs). Thus, immune surveillance is proposed to inhibit the outgrowth of MMR-deficient cell clones. Recent studies have shown that immunoediting during the evolution of MMR-deficient cancers leads to a counter-selection of highly immunogenic antigens. The immunogenicity of FSPs is dependent on the antigen presentation. One crucial factor determining antigen presentation is the HLA genotype. Hence, a LS carrier’s HLA genotype plays an important role in the presentation of FSP antigens to the immune system, and may influence the likelihood of progression from precancerous lesions to cancer. To address the challenge of clarifying this possibility including diverse populations with different HLA types, we have established the INDICATE initiative (Individual cancer risk by HLA type, http://indicate-lynch.org/), an international network aiming at a systematic evaluation of the HLA genotype as a possible cancer risk modifier in LS. Here we summarize the current knowledge on the role of HLA type in cancer risk and outline future research directions to delineate possible association in the scenario of LS with genetically defined risk population and highly immunogenic tumors.

Full paper – https://onlinelibrary.wiley.com/doi/full/10.1002%2Fijc.34312