Blog

Universal Germline Genetic Testing after a Diagnosis of Cancer

Age at diagnosis among patients with cancer is a predictor of pathogenic germline variant prevalence, yet age thresholds often misclassify genetic risk.

Findings support broad-based germline testing beyond conventional age-based criteria, reflecting the burden of hereditary risk even among late-onset cases.

Across 32 solid tumour types in a pan-cancer cohort, they found enrichment of germline pathogenic variants among patients with subtype-specific early-onset cancer. Using age 50 as a testing cutoff misses most patients with inherited predisposition, supporting universal germline genetic testing for all individuals diagnosed with cancer.


https://aacrjournals.org/cancerdiscovery/article-abstract/doi/10.1158/2159-8290.CD-26-0971/788729/Universal-Germline-Genetic-Testing-after-a

PPI seed funding

The purpose of the funding is to help patients, members of the public, patient and community organisations, and researchers work together on health and social care research.

Who can apply?

You can apply for Seed Funding if you are a:

• patient or member of the public

• researcher

• patient organisation

• community organisation

• charity

• organisation involved in health and social care research on the island of Ireland

Applicants must be based on the island of Ireland.

What kinds of activities could be funded?

The Seed Funding Programme is designed to be flexible. For example, you might ask for funding to:

• bring patients, members of the public and researchers together to explore a research idea

• involve patients or the public in developing a research funding application

• start a new PPI group

• develop a new partnership

• try a new way of involving people in research

• organise an event or activity that will help shape future research.

These are examples rather than a complete list.

ItaLynch: an ongoing Italian study to evaluate the feasibility of mainstreaming the diagnosis of Lynch syndrome in colorectal cancer patients

The ItaLynch project is an ongoing, prospective, observational, multicenter Italian clinical trial designed to evaluate the feasibility of mainstreaming genetic testing for Lynch syndrome (LS)

Highlights
  • •This is a prospective, observational, multicenter, multidisciplinary, Italian study.
  • •Investigating the feasibility of a new diagnostic algorithm for LS.
  • •A ‘Lynch alert’ in the pathology report is used as a clear warning to clinicians.
  • Proposing a shift to an oncologist-led mainstreaming genetic testing.
  • •This study encourages the establishment of multidisciplinary workgroups.

https://www.sciencedirect.com/science/article/pii/S2949819824000050

The implementation gap in aspirin chemoprevention for Lynch syndrome

How well is cancer prevention implemented in Lynch syndrome?

Report surveyed 539 individuals with Lynch syndrome and found:

🩺 99% reported undergoing colonoscopic surveillance.
💊 Only 7% used aspirin specifically for cancer prevention.
💉 80% expressed willingness to participate in a preventive cancer vaccine trial after receiving additional information.

The key message: High engagement in surveillance and strong interest in innovative prevention, but a substantial gap in translating existing evidence into clinical practice.

https://www.thelancet.com/journals/langas/article/PIIS2468-1253(26)00216-5/abstract

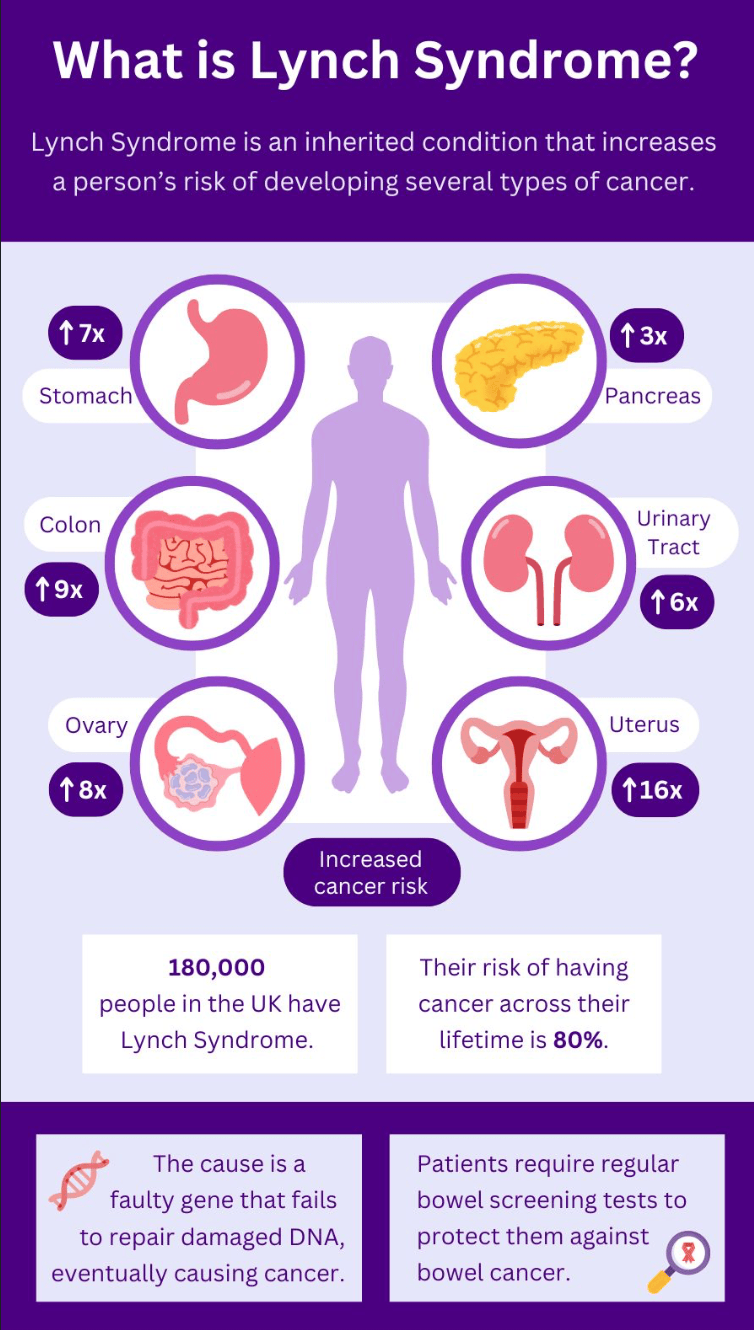
What is Lynch Syndrome?

Lynch syndrome is a hereditary condition caused by changes in the genes involved in repairing mistakes in our DNA. People with Lynch syndrome have an increased risk of developing several types of cancer, including bowel cancer.

Regular bowel surveillance is an important part of managing this increased risk. People with Lynch syndrome are currently recommended to have regular colonoscopies to look for and remove pre-cancerous changes, or to detect bowel cancer at an early stage.

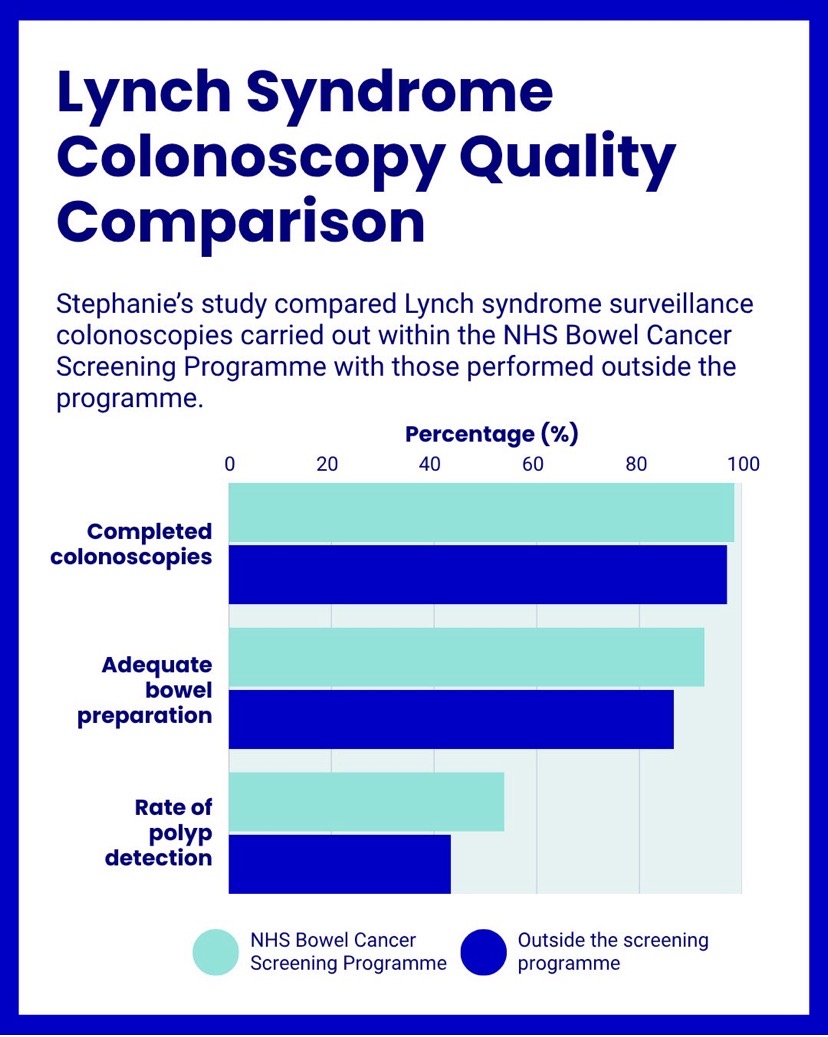
Findings of Lynch syndrome surveillance colonoscopies across the UK.

The authors conclude: “Lynch syndrome colonoscopy is generally being performed to a high standard, and procedures within the national screening programme appear to achieve particularly good quality and detection.”

If the population at large is to benefit from advances in genomic medicine, genetics services cannot do this alone

Outcomes from the English National Lynch Syndrome transformation project.

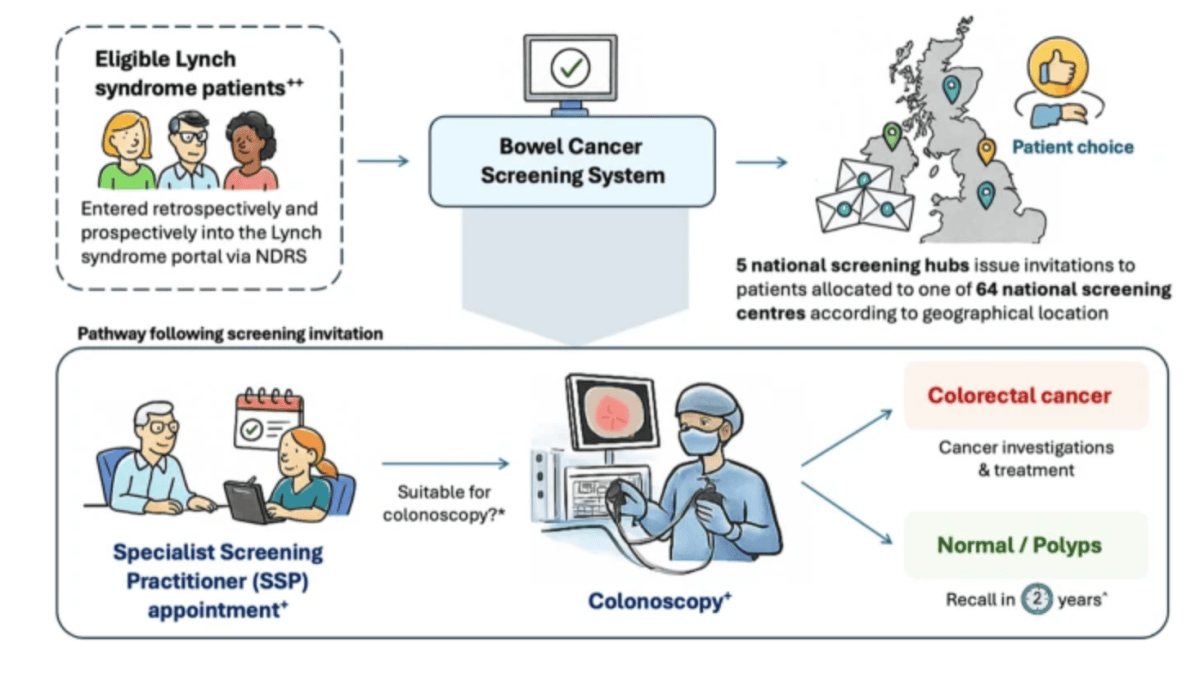
The NHS England LS Transformation project has driven equitable nationwide delivery of diagnosis testing for Lynch syndrome, with integration of ‘mainstreamed’ genetic testing into routine cancer care.

New diagnoses of LS have consistently increased each year from a total of 545 in 2020 to a total of 1394 in 2024 (an increase of 255% vs. a target of >50%).

https://onlinelibrary.wiley.com/doi/10.1002/ijc.70330

Don’t be embarrassed about your body.

At 42, Danielle Ripley-Burgess has survived colon cancer three times. She was first diagnosed at 17, then at 25 and then again at 39.

I don’t have any family history, and there was no explanation at first, but I found out I have Lynch syndrome, a genetic disease that puts you at a higher risk for several cancers, with colon and rectal cancers at the top of that list. I’m the first in my family to have the mutation.

If you’re seeing something with your body that’s uncomfortable and weird, and you’re not ready yet to tell a doctor, tell somebody — a friend or family member. Don’t sit in that place of: something is wrong with your body, and you don’t know what it is. Don’t sit there alone. Don’t downplay what you’re seeing.

https://www.today.com/health/womens-health/missouri-woman-survives-colon-cancer-3-times-lynch-syndrome-risk-rcna601664

ColoMARK initiative

Cancer is a major health problem in the European Union (EU), and colorectal cancer (CRC) is the third most prevalent tumour..

To combat this, the EU has enforced important R&D measures such as Europe’s Beating Cancer Plan and the EU Mission: Cancer. However, the alarming numbers of new reported CRC cases in the EU-27 and the lives it claims are expected to rise by 27% in the next two decades due to various factors.

To address this, we need immediate solutions to better prevent, treat, and manage CRC.


One solution is liquid biopsy, which allows for a less invasive way to assess tumor molecular features. Despite a plethora of published CRC biomarkers, there is still a need to identify and develop novel, clinically useful biomarkers that can improve disease outcome.

There are still many unknowns about the patient-specific biological determinants of tumour initiation and dissemination, or how clonality affects disease progression and response. In addition, the lack of standardisation and reproducibility of the assays and the need for biomarker research sustainability beyond a project are also issues.

https://www.colomark.org/colomark-overview

“Tell your family” sounds straightforward. But, in practice, it can be anything but.

In general this responsibility usually falls on the proband (the first person who undergoes genetic testing in the family). But every family is different.

When someone learns they have an inherited mutation in a cancer gene, that information is important for relatives. Because inherited mutations can be passed through families, a positive genetic test result may prompt relatives to consider testing of their own.

https://ambrygen.com/ambry/blog/29853/open-communication-talking-to-your-family-about-hereditary-cancer-risk?utm_campaign=HCT_Core&utm_content=386773808&utm_medium=social&utm_source=linkedin&hss_channel=lcp-110510