Conclusions:Among patients with resectable stage III or IV melanoma, event-free survival was significantly longer among those who received pembrolizumab both before and after surgery than among those who received adjuvant pembrolizumab alone. No new toxic effects were identified.
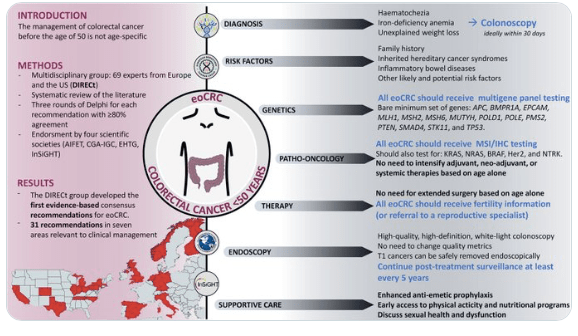
The DIRECt group produced the first consensus recommendations on eoCRC. All statements should be considered together with the accompanying comments and literature reviews. We highlighted areas where research should be prioritized. These guidelines represent a useful tool for clinicians caring for patients with eoCRC.
Results
The DIRECt consensus produced 31 recommendations for patients diagnosed with eoCRC ≥18 years old based on 145 articles (summarized in Supplementary Appendices 2–7). When appropriate, issues related to colon or rectal cancers specifically are highlighted; in cases where statements applied to both colon and rectal cancer, the term colorectal cancer (CRC) was used.
All statements are summarized in Table 2, Table 3, Table 4(Table 2: diagnosis, risk factors, and genetics; Table 3: pathology, oncology; Table 4: endoscopic diagnosis and treatment, therapy, and supportive care). Areas of controversy are described throughout the main text and summarized in Table 5.
Yes, it is possible to get life insurance after a cancer diagnosis. However, the availability and terms of coverage will depend on the specific details of your diagnosis, treatment, current health status and family history.
There’s no getting around the fact that life insurance after cancer is more expensive. If you can get cover, the insurer will increase your premium significantly compared to someone with no history of health issues.
Normally this increase will be temporary for a period of between one to ten years.
I’ve been given the gift of information,while it can be physically & emotionally taxing, I can take steps to ensure colorectal cancer doesn’t end my life.I can help others have the courage to get tested & go for screening if they notice a change.
When asked what she wanted people to take away from her contribution to the Marie Keating Foundation’s #JoinTheBowelMovement campaign this April, Roberta’s message was simple.
“Firstly, get to know your family history and the signs and symptoms of bowel cancer. Secondly, if you are experiencing symptoms but don’t fit the idea in your mind of “what a bowel cancer patient is”, speak to your GP about it anyway. And finally, if you’re eligible, go for BowelScreen. It’s so much easier to prevent than to cure, so if you were to take something away from my story, I would want it to be that.”
The leaders of those trials and other experts stressed that much more research is needed before this treatment approach becomes part of everyday cancer care. But they agreed that the findings so far are highly encouraging.
The most recent results come from a 35-patient clinical trial conducted at MD Anderson Cancer Center. Most patients in the trial had locally advanced colorectal cancer. Perhaps most important, however, was that all participants’ tumors had specific genetic changes—known as MSI-high or dMMR—that make them particularly good candidates for immunotherapy.