The method treats select cases of rectal cancer using only immunotherapy, which harnesses the body’s own immune system to fight cancer.
This allows some patients to skip standard of care treatment for rectal cancer which includes surgery, radiation, and chemotherapy, and can have life-altering consequences including infertility, incontinence, and more.
At ESMO in Madrid, Dr. Eduardo Vilar-Sanchez of MD Anderson presents long-term follow-up on NOUS-209, an investigational immunotherapy that trains the immune system to recognise Lynch-related cells before they become cancer. Carriers who received it were free of advanced adenomas and colorectal cancer on colonoscopy at one year and two years, and their immune responses grew stronger after annual re-vaccination. The program now has the funding and FDA Fast Track designation to move into a global registration-enabling trial.
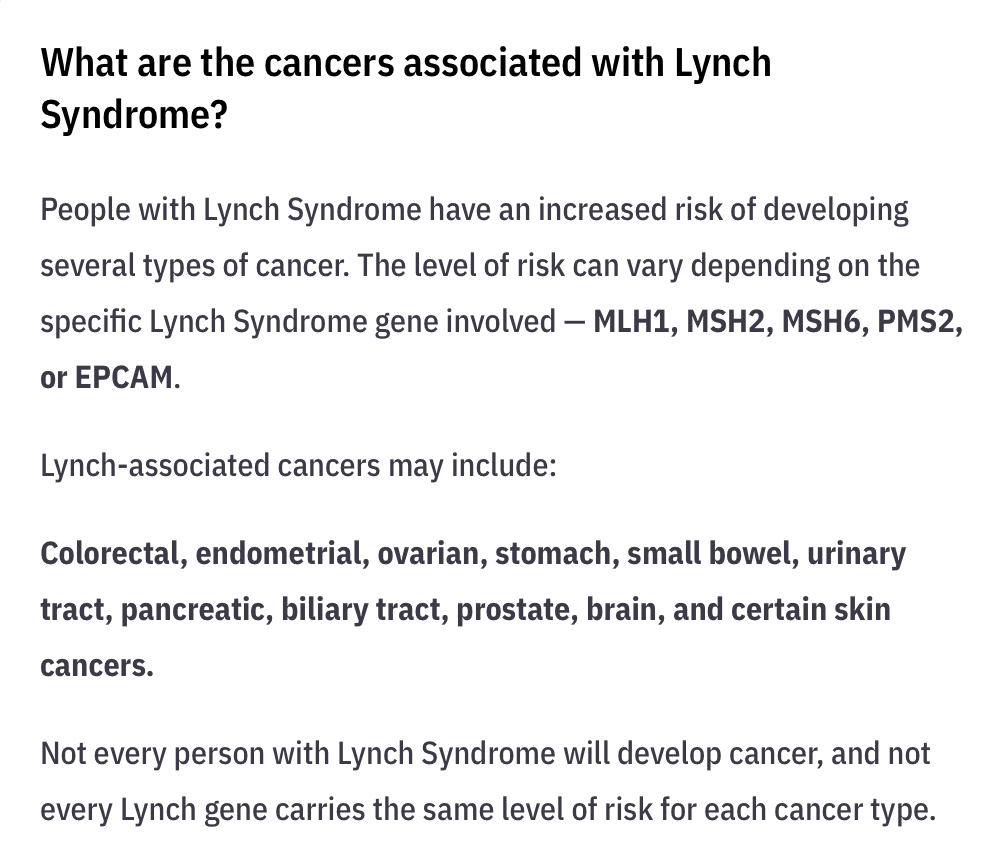
Lynch syndrome is a hereditary condition that substantially increases the risk of colorectal, endometrial and other cancers.
In a cohort expansion of the Phase I trial testing Nous-209, an investigational neoantigen-based vaccine designed to intercept cancer development in individuals with Lynch syndrome, researchers evaluated safety and outcomes following re-vaccination.
The study assessed two re-vaccination strategies, each administered one year after an initial vaccine series. Both approaches were well tolerated, with no severe side effects. Investigators reported enhanced T cell immune responses following re-vaccination, with the strongest immune boost seen in patients receiving a single neoantigen booster dose. In addition, no advanced colorectal cancers were detected in follow-up colonoscopies for study participants.
October is Menopause Awareness Month, a moment to talk openly about women‘s health in and after menopause.
One message matters for everyone: any bleeding after menopause should be checked by a doctor. It is the most common early sign of endometrial (womb) cancer, and acting on it early makes a difference.
For women with Lynch syndrome, endometrial cancer is one of the main cancer risks. That is why PREDI-ENDO, part of the PREDI‑LYNCH project, is testing whether non-invasive sampling can make endometrial cancer surveillance more acceptable and easier to access.
💙 Know your body, know your family history, and talk to your doctor.
Regular colonoscopies remain essential for people with Lynch syndrome, but repeated invasive procedures can be a real burden, and some people find them hard to keep up with.
PREDI-LYNCH is testing, alongside colonoscopy-based surveillance, whether non-invasive tests on blood, urine, stool and vaginal samples can make surveillance safer, more acceptable and more affordable.
🛡️ Protecting health while protecting peace of mind.
When facing uncertainty, start by asking two questions:
Am I viewing this uncertainty as a danger or an opportunity?
What type of uncertainty am I experiencing?
How we appraise uncertainty can influence how we feel, process information, and make decisions. If we view uncertainty as an opportunity, it can foster hope.
What this looks like in my life
For me, living with an inherited mutation involves medical uncertainty about my future cancer risk, familial uncertainty about what my genetic results mean for relatives, and financial uncertainty related to managing my risk.
Recognizing the different types of uncertainty helps me identify the questions I need to address and the support I need.
R = Reframe and Respond
What to remember
Uncertainty doesn’t have to be feared. It can be focusing.
Research suggests that uncertainty can focus our attention and motivate us to seek information or consider our options.
What this looks like in my life
When I tested positive, I expected that knowing my genetic predisposition would be empowering. And it has been, but at the same time, I quickly learned just having more information didn’t reduce my uncertainty about if I would be diagnosed with cancer like my mother, my aunt, and my great-great grandmother.
I couldn’t control my future cancer risk. But I could learn about my options, work with healthcare professionals, and make informed decisions about managing that risk.
Strategies to try
When facing uncertainty, consider the following strategies from your toolbox:
Seek information in a contained amount of time.
Distinguish what is known from what is unknown.
Connect with a trusted person.
Find a decision partner.
There is no single strategy that works for every person or every situation, and almost every day, I use different strategies. I seek reliable information, talk with my healthcare team, and connect with others.
T = Take Action
What to do
Work through the uncertainty by taking one small step with the information available.
Taking action also means recognizing that decisions may need to be revisited as circumstances and information change.
What this looks like in my life
For me, that includes following recommended cancer surveillance and making informed decisions with my healthcare team. Surveillance helps me act on what is known about my risk, even though it cannot tell me everything about my future.
When navigating uncertainty, I often return to my mother’s advice:
“You make the best decision you can with the information you have at that time.”
How wise.
While we can’t make decisions with information we don’t have, we can make thoughtful decisions with what we know now, learn from those decisions, and adjust when needed.
So, next time you feel unsure, make ART:
Assess uncertainty.
Reframe and Respond.
Take action.
We don’t have to wait for certainty to move forward. We can embrace uncertainty now.
A Decade of Patient Involvement – PVCR’s 10 Year Anniversary Convention.
Over the past decade, PVCR has initiated and facilitated trusted relationships between those with a lived experience of cancer and researchers; supported the education and training of both; ensuring that research priorities reflect the lived experiences, needs and expectations of people affected by cancer.
As they mark 10 years of impact, they want to acknowledge the communities whose insights have shaped our work while also looking ahead, strengthening the foundations for the next decade of sustainable, trust‑based research partnerships.
Nouscom, a Swiss biotech company, has raised €120 million (about $135 million) from investors to move its experimental cancer-prevention treatment into a large, final-stage clinical trial.
What the treatment is:NOUS-209 is an experimental “vaccine” designed to train the immune system to spot and destroy cells that are cancerous or on their way to becoming cancerous. It’s “off-the-shelf,” meaning it’s the same product for everyone rather than custom-made for each patient.
Who it’s for: People with Lynch Syndrome, an inherited condition that causes DNA-repair genes to malfunction. It affects an estimated two million people and raises the lifetime risk of cancer substantially (for colorectal cancer, up to about 50% versus 2% in the general population). Right now, the only options are frequent screening, such as colonoscopies, and preventive surgery, which is invasive. Screening doesn’t lower the chance of getting cancer; it just helps catch it early.
The early results: In an early-stage trial, people with Lynch Syndrome who received the vaccine stayed free of advanced precancerous growths and colorectal cancer, as checked by colonoscopy. This held for 43 people at one year and 17 at two years. Their immune systems also showed strong, lasting responses, which got stronger with yearly booster doses. The company says this looks promising compared to what would normally be expected in this population. The numbers are small, and there was no comparison group, so this is an encouraging signal rather than proof.
What happens next:
The new money will fund a single, global trial intended to support regulatory approval. The US FDA has given the treatment “Fast Track” status, which is meant to speed up development and review.
The latest data will be presented at a major cancer conference (ESMO) in Madrid on 25 October 2026.
NOUS-209 is also being tested in combination with another drug in patients who already have advanced colorectal cancer.
Who invested: The round was led by M Ventures and Revelation Partners. New backers include Angelini Industries, the European Investment Bank and Neva SGR, and all existing investors took part.
Bottom line:This is a promising but still experimental approach to preventing cancer in people at very high genetic risk. The funding allows the key late-stage testing to begin, but it’s not yet an approved treatment, and the larger trial will show whether the early results hold up.